Normal Ageing
- Misplacing keys, then retracing your steps to find them.
- Forgetting a name and recalling it a little later.
- Pausing to find the right word now and then.
- An occasional slip with a bill or a date.
Introduction
to the Tata Trusts
Know the
work we do
Discover our impact
stories and campaigns
Publications
and reports
In the media
Opportunities
for impact






Dementia is not a single illness. It is an umbrella term for a group of conditions that damage brain cells and disrupt the networks they form. Most people think of it as memory loss, but that is only the surface. Over time, dementia erodes thinking, behaviour, judgement and the ability to live independently. It is a progressive, neurodegenerative condition caused by structural and chemical changes in the brain — and it is not, as many families assume, an ordinary or natural part of ageing.
Understanding it clearly is the first step, because a condition that is understood can be planned for, supported and managed for an improved quality of life.
Most common cause globally; typically starts with progressive memory loss, later affecting other cognitive domains.
Due to stroke, small vessel disease, and chronic reduced brain blood flow; strongly linked to hypertension, diabetes, high cholesterol, smoking, and cardiovascular disease; a major contributor in India.
More common in younger-onset dementia (often 45—65 years); early changes in personality, behaviour, and/or language, with memory relatively preserved initially.
Core features include fluctuating cognition/alertness, recurrent visual hallucinations, REM sleep behaviour disorder, and parkinsonian movement problems.
Some forgetfulness comes naturally with age. So, how do you tell dementia from normal forgetfulness? It's different in kind, not just degree, and telling the two apart is what makes early action possible. Not every memory lapse is dementia, but a persistent pattern of dementia symptoms in older adults is worth checking.
Dementia is already one of India's largest unrecognised health challenges. Since only a few cases are ever diagnosed, the true scale remains hidden inside homes — quietly accepted as a normal part of ageing.
Dementia rarely stays a personal medical problem. What begins with a single person ripples outward, through the family, the workplace, the health system and, eventually, the economy. This is why dementia deserves to be treated as a shared responsibility rather than a private difficulty, and why support that reaches the whole household matters as much as treatment for one person.
This condition doesn't take life first. It takes:
It results in:
It causes:
It enters the system:
Put together, the ripple becomes national:
Dementia extends far beyond memory loss. The various dimensions of loss experienced by a person living with dementia include the loss of the ability to perform everyday tasks such as cooking, managing finances and taking medication; loss of one's position within the family, including as a provider, decision-maker or teacher; loss of independence, including the inability to navigate familiar places without supervision; withdrawal from family rituals and community participation; and, ultimately, loss of recognition of family, spouse and self.
These dimensions do not disappear all at once. They erode progressively, often beginning with changes to everyday function and roles and ultimately affecting autonomy, social participation and sense of self.
The paradox of identity loss is that it is felt most acutely when cognitive awareness is highest in the early stages. As dementia progresses, the person gradually loses the ability to perceive their own loss.
Not in a clinic, but in the kitchen, on the daily walk, in a question asked one too many times. This is what families actually see, long before anyone thinks about calling it a disease.

A dish cooked for forty years suddenly comes out wrong, step after step.
The way to the market — walked a thousand times — stops making sense.
Everyday things turn up in impossible places, over and over.

“When are we leaving?” asked five times in ten minutes, each time new.

Asking for tea minutes after finishing a cup — the memory of it simply isn't there.
Stepping back from people and rituals once loved. Often mistaken for mood.
Memory loss that disrupts daily life.
Repeating questions or stories.
Confusion about time or place.
Poor judgement or unusual decisions.
Trouble following a familiar recipe or route.
Difficulty with money, bills or simple sums.
Changes in mood or personality.
Misplacing things and putting them in odd places.
Losing the thread of a conversation.
Withdrawing from work or social life.
If some of these symptoms sound familiar and are taking place persistently, it is worth consulting a medical practitioner. Click here to know more.
The person caring for the patient, most often a spouse, child or daughter-in-law, slowly becomes a second, often unseen, person carrying the weight of it all. Caregiving demands skill and extensive effort, yet its cost is almost never accounted for.
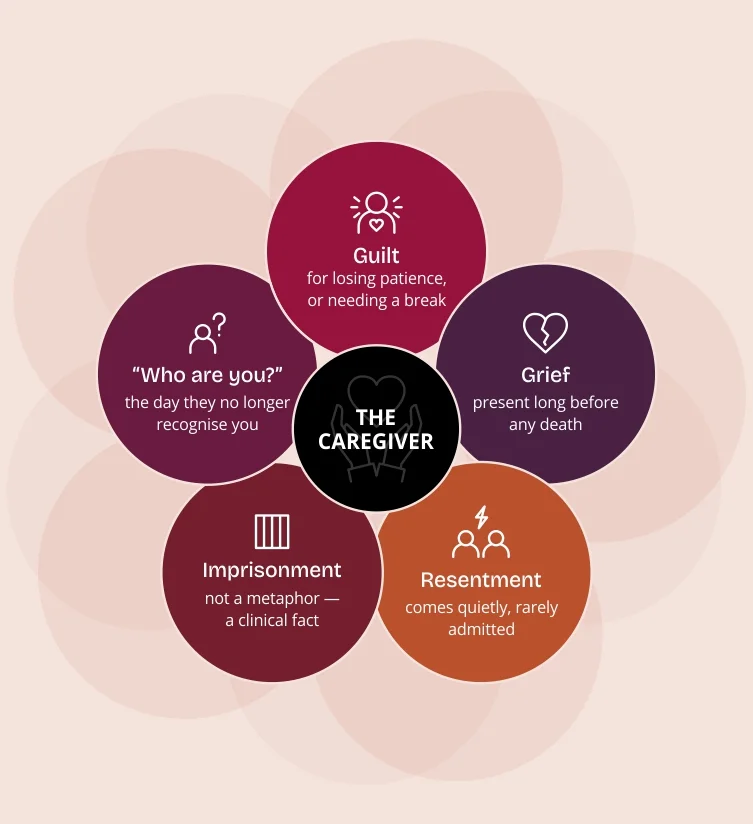
Five feelings that come with caring for someone living with dementia — and why feeling all of them at once is normal.
These are the dominant emotions a caregiver moves through. They coexist, they collide, and they can exist within the same hour.
None of this is a failure of love. It is the weight of the work — and it is a reason to ask for support, not to feel ashamed.
The good news: A caregiver doesn't have to figure this out alone.
Guidance, training and support groups for caregivers are a call away. Click here to know more.
What screening involves

Most screening tools take 5–15 minutes and involve questions and simple tasks: remembering words, drawing a clock, naming objects, solving small problems.

No needles or scans are needed for the initial screen. It is a conversation, plus paper-and-pen or tablet-based tasks.

Results are shared privately with you and, if you wish, with a family member. The goal is support, not judgement.

A screening test indicates whether further evaluation by a physician, neurologist or geriatric specialist, is needed.

Based on your results and health history, you will get practical advice: managing blood pressure, diabetes and cholesterol; staying physically active; eating well; improving sleep; stopping smoking; limiting alcohol; and staying socially and mentally engaged.

If the screen suggests possible cognitive changes, you will be offered counselling on what this means, how to plan ahead, and how to access medical, psychological and caregiver support. Even when no diagnosis is made, you can discuss your personal risk factors and receive a tailored plan to reduce your long-term risk of dementia.
Click here to know more.
A large share of dementia risk is linked to things we can act on, starting in midlife, long before any symptoms appear.
Protecting the brain when we are young, shapes the mind at a later stage.
of cases may be preventable or delayable by acting on modifiable risk factors
Source: Lancet



“Dementia will be one of the defining health conversations in India over the next three decades. Our effort is to build a shared, evidence-based understanding of dementia in India, one that looks beyond the disease to the realities of the individual and the caregiver and seeks to build an ecosystem of care around them.”
— Mr Siddharth Sharma
CEO, Tata Trusts

“People often describe changes in memory, behaviour or everyday functioning simply as old age. But these changes can be early signs of dementia and should not be dismissed. While there is currently no cure for dementia, an early diagnosis can be transformative. Literature on the subject underscores a critical health prevention window and we need to utilise that through systemic action on modifiable risk factors such as diabetes, hypertension and other lifestyle factors.”
— Dr Anura Kurpad
Senior Advisor, Health and Nutrition, Tata Trusts

“Early detection of dementia is an important first step, but it cannot exist in isolation. India today has fewer than 50 full-fledged dementia care centers. We need a stronger, more connected dementia ecosystem, one that supports individuals and caregivers, equips families with resources and knowledge to navigate this difficult journey, and brings healthcare, communities, workplaces and policymakers together to respond proactively and effectively.”
— Ms Ramani Sundaram
Executive Director, Dementia India Alliance

“The next decade offers a critical opportunity to act. The development ecosystem can help by piloting models, generating evidence and building scalable solutions that ensure ageing is not associated with vulnerability, but with dignity, security and continued participation in society.”
— Mr HSD Srinivas
Head – Health Initiatives, Tata Trusts
What can we do to prevent families from misattributing symptoms of dementia to old age and seeking early intervention?
The campaign takes this question into homes across India - through films, posters and stories.
Watch the film
Explore the campaign assets below.